Beds Are Shrinking, and Care Is Expanding Beyond the Hospital
[Key Message]
* Care outside the hospital is not about convenience, but about the survival of the healthcare system. As aging, chronic disease, staffing shortages, and bed pressure intensify, expanding treatment beyond the hospital is becoming not an option but a structural response.
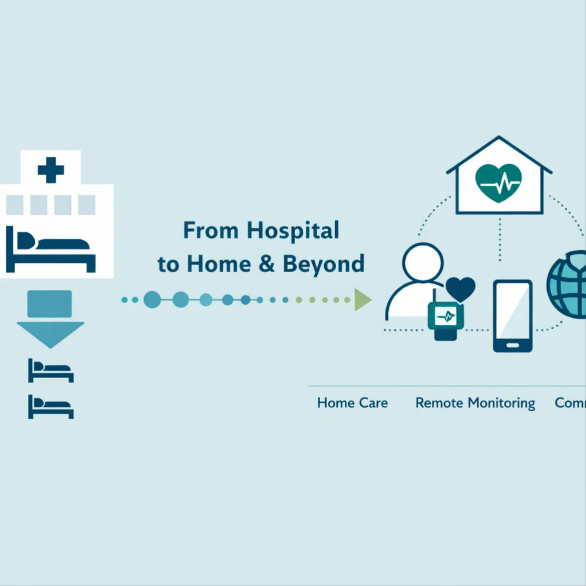
* Hospitals are no longer spaces that hold every patient, but spaces that concentrate on the most critical ones. Hospitals are increasingly focusing their capacity on emergencies, intensive care, and high-complexity treatment, while recovery care and chronic disease management move into the home and the community.
* The home is evolving from a place of recovery into an institutional space of treatment. As home-based care, visiting care, and remote monitoring are combined, the gap after discharge is narrowing and continuity of treatment is being sustained even at home.
* The success of care outside the hospital depends more on systems and operations than on technology. More important than wearables or apps are patient selection, crisis-response protocols, staffing, reimbursement, and connections with community care.
* The future competitiveness of healthcare will depend less on the number of beds and more on how safely patients can be managed at home. In the future, the strength of hospitals and healthcare systems will likely be judged less by how many large facilities they have and more by how well they can monitor and protect patients after discharge.
***
For a long time, hospitals were the center of treatment. The structure in which a patient was admitted when their condition worsened and discharged once stabilized was regarded as the basic grammar of medicine. But the healthcare of the future will not follow that simple line. Treatment will no longer take place only inside hospital rooms; it will continue outward into homes, local communities, and everyday spaces connected by digital devices after discharge. That is why home-based care and remote monitoring are becoming so important. This is not merely a change in which a few convenient services are added. It is closer to a movement in which a hospital-centered system acknowledges its own limits and changes the way it operates. Around the world, rapidly aging populations and growing demand for chronic disease management are making it harder to meet healthcare needs with beds and staffing alone.
Why is this change growing? The biggest background factor is the expansion of aging and chronic illness. Increasingly, the patients healthcare systems must care for are not those whose treatment ends with a single hospitalization, but those who must be watched over for a long time and require repeated intervention. More patients now live with conditions such as heart failure, diabetes, chronic respiratory disease, frailty in old age, postoperative recovery, and post-cancer follow-up—conditions that may remain unstable but do not necessarily require prolonged stays in a hospital ward. At the same time, there are not enough personnel to operate hospital beds, and financial resources are not unlimited. As a result, healthcare is moving away from keeping all patients inside hospital buildings for long periods and toward compressing only the time that truly must be spent in the hospital, while continuing the rest of treatment outside. The expansion of virtual wards and hospital-at-home models in countries including the United Kingdom, the United States, and Canada reflects the same recognition.
The Role of the Hospital Becomes Clearer
This change does not mean that hospitals are becoming weaker. Rather, it is closer to a process of distinguishing what hospitals do best from what they do not. Emergency response, intensive care, surgery and procedures, and concentrated treatment for acute deterioration must still take place inside hospitals. But a structure in which wards also take full responsibility for every stage of recovery, observation, and follow-up is becoming increasingly inefficient. In the future, hospitals are likely to become places of shorter but more intensive treatment, while recovery and follow-up extend outward beyond their walls. Hospitals are being redefined not as buildings in themselves, but as core hubs that deliver high-density care when it is needed.
Seen this way, home-based care and remote monitoring are not low-cost policies aimed simply at reducing admissions. They are operational techniques for keeping beds available for patients who truly need hospital care. Many countries are under pressure to use bed capacity more efficiently. What matters is not expanding beds without limit, but developing the ability to distinguish precisely which patients must remain inside the hospital and which can be managed outside it. A hospital bed is a physical space, but in practice the success or failure of healthcare depends less on where a patient is placed than on how intensely they are monitored and how effectively intervention takes place. For that reason, the competitiveness of hospitals in the future is likely to be judged not only by surgical volume or the scale of their equipment, but also by how stably they can keep patients connected to care after discharge.
Another important change is that the very meaning of admission and discharge is changing. In the past, discharge was close to a signal that treatment was nearly complete. But now discharge is becoming not the interruption of care, but a change in the method of management. Once direct monitoring inside the hospital ends, indirect monitoring at home and early intervention begin. For elderly patients and those with chronic disease in particular, the first few days and weeks after discharge are often the most unstable period. Readmission is often less a sign that treatment inside the hospital failed than a sign that the thread of care extending beyond the hospital had become too loose. That is why modern healthcare is beginning to view the post-discharge period not as separate aftercare, but as part of treatment itself.
To say that the role of the hospital becomes clearer does not mean that hospitals will have less to do. On the contrary, it means that they will be forced to concentrate on more difficult work. At a time when hospitals must intervene faster and more deeply for critically ill patients, emergency patients, and those needing high-complexity procedures, if they continue to hold on to less critical patients for too long, resources may become insufficient at the very moments of greatest danger. In that sense, the expansion of care outside the hospital is not a movement to replace hospitals, but one that preserves their core function. The ability to empty the hospital when it should be emptied, and to keep patients there when they must remain, is likely to become one of the key standards dividing strong healthcare systems from weak ones.
The Home Becomes Not Only a Place of Recovery but a Place of Treatment
The home is, by nature, a place favorable to recovery. Familiar surroundings, the preservation of daily routines, proximity to family, and psychological stability are all sources of healing that hospital rooms cannot easily provide. For older adults in particular, an unfamiliar hospital environment can itself cause confusion and functional decline. Prolonged hospitalization can lead to muscle loss, sleep disruption, delirium risk, and emotional withdrawal, and can become another health risk in its own right. So for some patients, staying longer in the hospital is not necessarily the better treatment. The problem is that although the home has long been a place of recovery, it has not been fully recognized institutionally as a place of treatment.
In the past, healthcare systems often left the post-discharge period largely to patients and families. Once discharge education was given, prescriptions were written, and the next outpatient appointment scheduled, the hospital’s role was often treated as essentially complete. But reality is not that simple. Patients returning home may fail to take medication correctly, or may have difficulty judging warning signs such as sudden shortness of breath, weight gain, swelling, or fever. Even when a caregiver is present, a lack of medical knowledge can make it hard to decide whether to go straight to the emergency room or wait and watch a little longer. In that interval, the condition worsens, and repeated readmissions follow. The institutionalization of care outside the hospital is an effort to reduce precisely this gray zone.
To say that the home is becoming a place of treatment does not mean merely that a doctor has a video call once. It means a system in which signals such as blood pressure, blood glucose, body weight, heart rate, and oxygen saturation are continuously tracked; when abnormalities are detected, clinicians intervene first; and if necessary, home visits by doctors, visiting nursing, medication adjustment, and even emergency transfer are connected. In other words, the home is not imitating the hospital. Rather, it is receiving part of the hospital’s monitoring function while preserving the advantages of being home. Treatment is not simply moving from the hospital to the house; the boundary of treatment itself is being extended.
The patient groups for whom this model is especially effective are relatively clear. They include patients in recovery after acute deterioration has passed and their condition has stabilized to some degree, patients requiring long-term monitoring for chronic disease, elderly patients at high risk of readmission shortly after discharge, and patients whose frailty means that hospitalization itself poses another risk of complications. For these patients, what matters is not remaining in the hospital longer, but not missing changes in condition after returning home. Care outside the hospital should not be understood as automatically lowering the intensity of treatment, but rather as lengthening the period during which treatment remains actively sustained.
As the home becomes a place of treatment, healthcare ceases to be a service centered on buildings. It becomes a service that follows the course of a person’s life. This transformation also has a major impact on patient experience. Receiving treatment at home is not merely a matter of convenience. Patients can recover in a way that is closer to their own daily rhythm rather than the timetable of a hospital, and families can understand changes in condition more directly. Of course, caregiver burden may increase, but in a well-designed system it can instead offer a more stable recovery experience for both patients and families. In the end, to say that the home is becoming a place of treatment is also to say that healthcare is beginning to come to the patient.
An Era in Which Data Watches in Place of the Bed
The core of care outside the hospital lies less in changing location than in changing the method of observation. In the past, hospitals gathered patients into one space and watched them with the human eye. Nurses checked vital signs at set intervals, and physicians made rounds to assess condition. The healthcare of the future is shifting toward a system that keeps patients dispersed but continuously visible through data. Even when a patient is not lying in a hospital bed, that patient does not completely disappear from the medical field of vision. This means that hospitals are moving from a model of surveillance centered on physical space to one centered on connected information.
The meaning of this shift is not simple. Changes such as rapid weight gain over several days, falling oxygen saturation, or unstable heart rate can appear before the patient subjectively feels that something is seriously wrong. For patients with heart failure, chronic lung disease, diabetes, or frailty in old age, whose conditions often worsen gradually, detecting such subtle signals early is critically important. In the past, hospitals often intervened only after patients arrived in the emergency room short of breath or after symptoms had already worsened. Now it is becoming possible to detect warning signs before symptoms explode, adjust medication first, or connect a home visit before the situation becomes severe. The center of gravity in medicine is moving from response after the fact to intervention in advance.
Virtual wards and hospital-at-home models spreading abroad are precisely the institutionalization of this idea. Patients are at home, but within the system they are managed almost like distributed hospital beds. In other words, the concept of a bed no longer refers only to a bed inside a hospital building. Healthcare is being reorganized around not “Where should the patient lie?” but “How can we avoid missing the patient’s condition?” This shift is likely to lead from competition over the number of beds themselves to competition over whether hospital-level observation and response can be maintained even outside the hospital.
But more data does not automatically produce better care. Data is only a signal; it becomes meaningful only if a system exists to interpret it and translate it into action. Who will look at the numbers coming in dozens of times a day? What changes in those numbers require immediate response? When an alert goes off, should the patient be called, should a visit be sent, or should emergency transfer be arranged? These judgment structures matter. If data merely accumulates without corresponding response, patients do not become safer; they may instead be left inside the illusion that they are being managed.
That is why, in care outside the hospital, the sophistication of the operating system matters more than the spread of digital devices. When studies from abroad are considered together, this model appears feasible for certain patient groups, tends to show high patient satisfaction, and has the potential to ease pressure on hospital beds. But lower costs or reduced readmissions do not automatically follow in every context. In the end, the key is not whether technology exists, but how dense and careful the design is. Who is selected, how intensively they are monitored, and what criteria are used for crisis response determine success or failure. Care outside the hospital is less a passing technological trend than a form of highly detailed operational medicine.
More Important Than Technology Are Institutions and People
When many people hear about remote monitoring, they first think of wearable devices, apps, or video consultation platforms. But in practice, the hardest issue is not equipment but people. Who will select patients for care outside the hospital? At what point should they be transferred back into the hospital? Who will respond at night or on weekends? Who will review the data gathered at home every day? Inside hospitals, familiar procedures and staffing structures operate with relative stability. Outside hospitals, all of this must be newly designed. If institutions are not dense and well-built, home-based care becomes not an extension of treatment but a void of responsibility.
This also involves changes in the roles of healthcare professionals. As care outside the hospital expands, physicians cannot remain limited to seeing patients inside exam rooms. Nurses become not merely providers of procedures, but key actors who detect changes early, educate patients, and connect the hospital with the home. Pharmacists can help improve medication adherence and detect adverse effects early, while community care workers support non-medical conditions such as meals, transportation, and daily functioning. In the end, care outside the hospital does not make healthcare weaker; it creates a structure that demands more professions and more connections. As treatment moves outside the hospital, the density of collaboration actually has to increase.
Another core issue is insurance and reimbursement. Inside hospitals, visible acts such as bed use, procedures, tests, and surgery are relatively clearly reimbursed. But care outside the hospital is not so simple. Time spent reviewing data remotely, checking on patients by phone, coordinating visiting nurses, and linking patients with community care services requires substantial labor, yet may not be adequately reflected in existing payment systems. If this is not addressed, healthcare institutions will have little incentive to expand care outside the hospital, and even if the goals are widely supported, the system may fail to become sustainable. The institutionalization of care outside the hospital is therefore not just a question of whether technology is permitted, but of redesigning reimbursement and responsibility.
This transformation also carries clear risks. The home may be the best place of recovery for some patients, but for others it may be the most vulnerable place. For elderly people living alone, those unfamiliar with digital devices, households lacking family caregiving capacity, or patients living in unstable housing, care outside the hospital can actually increase instability. The fact that numerical readings are coming in remotely does not in itself guarantee safety. If a patient is not eating properly, misses medications, or has no one to call for help in an emergency, technology reaches its limit. That is why care outside the hospital cannot be completed by medical services alone. Long-term care, visiting nursing, community support, housing assistance, communication infrastructure, and data privacy protection must all move together.
Ultimately, the reason institutions and people matter more than technology is that care outside the hospital is not a scaled-down version of medicine, but an expanded version of it. Inside the hospital, a single institution took responsibility for much of care. Outside the hospital, multiple institutions and professions must be reconnected around one person’s life. This is not merely a question of digital health, but something closer to a test of society’s overall capacity for coordination. The farther healthcare moves beyond the hospital, the more states are asked for coordination capacity and communities for collaborative strength. That is why the institutionalization of care outside the hospital is both healthcare policy and social policy.
What Overseas Systems Have Already Shown, and What Korea Will Soon Face
If one looks at examples abroad, the direction is relatively clear. The United Kingdom has expanded a model in which part of hospital-level acute care is shifted to the patient’s place of residence through virtual wards. The United States has experimented through hospital-at-home programs to determine which patient groups can safely receive hospital-level treatment at home and under what conditions this can be run safely. Canada, Australia, and other countries are also expanding models that combine home-based acute care, intensive follow-up after discharge, digital monitoring, and home visits. Institutional and financial arrangements differ from country to country, but the common direction is unmistakable. The point is not to eliminate the hospital’s function, but to divide more precisely the segment that hospitals must handle from the segment that can continue outside them.
What overseas studies and policy trends show can be reduced to two essentials. First, care outside the hospital is sufficiently feasible for appropriately selected patients. Second, success depends more on operations and support systems than on technology itself. Patient satisfaction is often relatively high, and in some settings such models can help ease bed pressure or improve the experience of recovery. But costs do not always fall dramatically, nor do readmissions automatically decline in every case. Therefore, care outside the hospital should be seen not as a magical answer, but as a carefully engineered solution that works when well designed.
Korea is not a country untouched by this trend. In fact, it faces even greater pressure. Rapid aging, concentration on major hospitals in the Seoul metropolitan area, shortages of regional medical staff, and the weakening of family caregiving capacity are all progressing at once. The era is approaching in which building more hospitals and adding more beds will no longer be enough. For that reason, home-based care, home visits, remote monitoring, and integrated community care are likely to be discussed more and more as one connected package in Korea as well. Trends that appeared earlier abroad are likely to emerge as even more urgent problems in Korea.
In particular, Korea has relatively high hospital accessibility and a strong culture of using large hospitals, so the institutionalization of care outside the hospital will not be resolved merely by adopting technology. Patients and families must be able to feel hospital-level safety even outside the hospital, and healthcare professionals must also have clear standards and reimbursement structures for taking responsibility after discharge. In that sense, Korea needs not simply to copy overseas models, but to examine where those systems succeeded and failed, and then design its own institutions more carefully. Overseas materials matter because Korea is already standing before very similar problems.
The Coming Shift: From Competition Over Beds to Competition Over Management Capacity
One of the most important changes in global healthcare over the next several years is likely to be that the ability to substitute for beds becomes a more important indicator than the number of beds itself. Hospitals will still matter, but systems that are weak at managing patients outside the hospital will find it difficult to endure continuing pressure on beds. By contrast, systems that can safely hold patients in homes and communities will be able to absorb greater demand with the same number of beds. In the end, the future of healthcare is likely to move less toward expanding physical space and more toward refining operations. The competition will no longer be over who can build the bigger hospital, but over who can maintain hospital-level continuity even outside it.
Another prediction is that care outside the hospital will not remain a passing fashion tied to a specific technology, but will increasingly become the standard model for post-discharge management. This change is likely to appear first and fastest among the elderly, people with chronic disease, frail patients, and those in recovery. Time spent in beds will become shorter, while the period of management at home becomes longer. In that process, hospitals will focus more on surgery, emergency response, and high-complexity procedures, while the success of healthcare will depend increasingly on how stably the first week and first month after discharge are managed. An era is coming in which the ability to connect care after discharge matters more than admission itself.
At the same time, new inequalities may emerge. There is a risk of creating a structure in which only patients who can transmit data well are clearly visible, only those able to handle digital devices can be easily managed, and only households with family caregiving resources can enjoy the greatest benefits. That is why the real contest in the future may not be the speed of technological adoption, but the ability to reduce the number of people pushed outside the system. If the hospital is successfully emptied but the burden of care is simply moved into the household, that would not be innovation but a transfer of cost. The institutionalization of care outside the hospital is likely to be judged less by quantitative expansion than by the quality of its design.
Finally, one can expect the way medical institutions compete to change. Until now, hospital competitiveness has often been judged by indicators such as the number of physicians, surgical volume, advanced equipment, and brand image. In the future, one more criterion may be added: the ability to manage discharged patients for a long time, safely, and in a humane way. Institutions that are capable not only inside the hospital, but across the patient’s entire path of care extending beyond discharge, may earn greater trust than those that excel only within their walls. In the end, healthcare is likely to move from being hospital-centered to being patient-pathway-centered, and care outside the hospital may become one of the most symbolic scenes of that transformation.
Ultimately, the institutionalization of care outside the hospital is not a process of shrinking medicine. On the contrary, it is an effort to ensure that hospitals can operate more powerfully at the moments they are truly needed, while connecting patients’ daily lives and their treatment over a longer span of time. We are moving from an era in which the hospital was the whole of treatment to one in which the hospital becomes the core hub, and care extends far beyond it. The competitiveness of future healthcare is likely to be judged increasingly not by the number of large buildings, but by how safely patients can be protected at home. The era of expanding beds is giving way to an era of continuing treatment even without them.
Reference
World Health Organization. 2025. Ageing and Health. Geneva: WHO.
OECD. 2025. Health at a Glance 2025: OECD Indicators. Paris: OECD Publishing.
NHS England. 2024. Virtual Wards Operational Framework. London: NHS England. Updated July 4, 2025.
Cathers, Shelley, and Clare Lally. 2025. Virtual Wards and Hospital at Home. POSTnote 744. London: Parliamentary Office of Science and Technology, UK Parliament. Published April 28, 2025.
Edgar, Kirsty, Mark Shepperd, Helen Williams, Iain A. Langhorne, and colleagues. 2024. “Admission Avoidance Hospital at Home.” Cochrane Database of Systematic Reviews 2024, no. 2: CD007491.
NIHR Evidence. 2025. Hospital at Home and Virtual Wards: What Works? National Institute for Health and Care Research, March 31, 2025. ([NIHR Evidence][6])
Levine, David M., Meghna P. Desai, Sarah Barthel, and colleagues. 2025. “Hospital-Level Care at Home for Adults Living in Rural Settings: A Randomized Clinical Trial.” JAMA Network Open 8, no. 12: e2545712.
Centers for Medicare & Medicaid Services. 2024. Report on the Study of the Acute Hospital Care at Home Initiative. Baltimore, MD: CMS. Fact sheet released September 30, 2024.